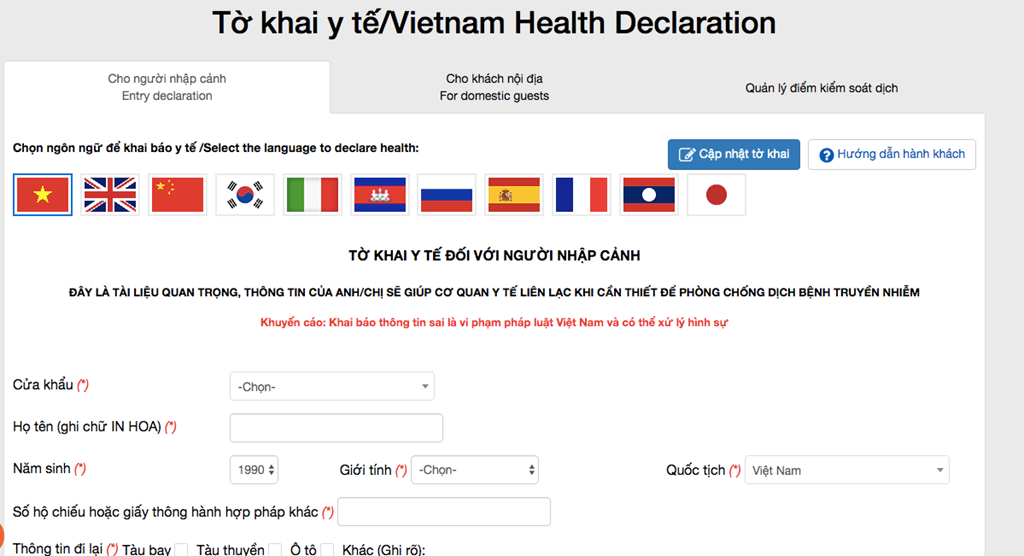
MEDICAL DECLARATION FORM IN VIETNAM
MEDICAL DECLARATION FORM
This is important document, your information is vital to allow health
authorities contact you to prevent communicable diseases
Click here to download: MEDICAL DECLARATION FORM
Full name (BLOCK LETTERS): …………………………………………………………………………….
Date of Birth: …………………… Gender: …………….. Nationality: …………………………
Passport number or other legal document: ………………………………………………………………………..
Travel information: Plane £ Ship £ Automobile £ Other (clarify): …….……………………..
Transportation No.:……………………….…… Seat No.:………………………………………….
Departure date: ……. /……../…………….. Immigation date: ……. /……../……………………………………..
Place of departure (province/country): ……………………….…………………………………..
Place of destination (province/country): ..………….……………………………………………..
In the past 14 days, have you been to any province/city/territory/country? If yes, where?:
Contact information in Viet Nam
Staying address:…………………………………………………………………………………………………..
Tel./Mob.: …………………………………….Email: …………………………………………………
If you have any of the followings at present or during the past 14 days (until the date of entry/exit/transit)?
|
Symptoms |
Yes |
No |
Symptoms |
Yes |
No |
| Fever
Cough Difficulty of breathing Sore throat |
[ ] [ ] [ ] [ ] |
[ ] [ ] [ ] [ ] |
Vomiting
Diarrhea Rash Skin haemorrhage |
[ ] [ ] [ ] [ ] |
[ ] [ ] [ ] [ ] |
List of vaccines or biologicals used: ……………………………………………………………………….
History of exposure: During the last 14 days, did you:
| Visit any poultry farm/ living animal market/ slaughter house/ contact to animal | Yes [ ] No [ ] |
| Care for a sick person of communicables diseases | Yes [ ] No [ ] |
The information I have given is true, correct and complete. I understand failure to answer any question may have serious consequences.
| Day: Month: Year: 202.. | Signature of Passenger/ Crew |
GUIDANCE
| Passenger uses this part for entry/exit/transit clearance and for protection of your health
Full name (BLOCK LETTERS): ………………………………………………… Province/City/Territory/Country of departure: …………………………………. |
|
|
VERIFICATION BY
Date Month Year 202… |
For your own heath and that of the community, if you experience any of the above-mentioned symptoms, please contact heath quarantine units at points entry or the nearest healthcare centre or email to Email: kdytqtbrvt@gmail.com or Fax: 0254.3838987
Hotline of province/city of point of entry: 0913.684195 Dr. Pho Đuc Thang Hotline of the Ministry of Health: … |